Corneal ectasia screening program for ophthalmologists
Corneal ectasia screening before LASIK and PRK
CER-AI supports preoperative laser eye surgery screening by organizing Pentacam measurements, independent ectasia-risk assessments and procedure-specific tissue-safety calculations for surgeon review. It is a web-based professional tool for the refractive surgery assessment workflow.
What does the surgeon upload and receive?
- Inputs: OD and OS Pentacam 4 Maps Refractive and BAD Display images, plus one Show 2 Exams Topometric comparison; surgeon-confirmed clinical and refractive information completes the assessment.
- Risk review: Randleman ERSS, Pentacam Final BAD-D, CER-AI-adapted NICE and PS3 are shown separately with reasons and warnings.
- Planning review: LASIK or PRK tissue-safety checks are presented alongside the risk assessment, using the selected procedure and treatment parameters.
- Output: an explained assessment report for the surgeon to review, print or share.
Preoperative screening software supports the examination; it does not replace it or guarantee that an eye will remain free of ectasia. Read the clinical evidence and validation limits and worked synthetic examples before requesting access.
Independent ectasia assessment platform — currently free access
CER-AI is a standalone web platform for corneal ectasia risk assessment before LASIK and PRK, including review of risk factors associated with post-LASIK ectasia. It runs outside the imaging device's software.
Device-associated tools include the Belin/Ambrósio Display (BAD) in the Pentacam software ecosystem and the SCORE Analyzer on the ANTERION imaging platform. Access to these tools requires the relevant imaging system and applicable software configuration or licensing; equipment and license costs vary by supplier and configuration.
CER-AI adds a separate workflow using existing supported Pentacam reports. It does not replace tomography hardware or generate BAD-D without the device report. Current compatibility is defined for Pentacam sources; support for every imaging device is not claimed.
Current access is free for approved physicians. New demo accounts have a 10-patient allowance and require approval. A low-cost physician subscription is planned for the future; no final tariff or start date has been announced.
OCULUS Pentacam software · Heidelberg Engineering ANTERION workflows
What is laser vision correction?
Laser vision correction includes procedures such as LASIK and PRK. CER-AI supports AI-assisted preoperative assessment before laser eye surgery: Pentacam image reading, keratoconus and ectasia risk review, and corneal tissue-safety checks.
Does AI-assisted laser vision correction mean AI performs the operation?
No. AI-assisted laser vision correction here refers to decision support before LASIK or PRK. CER-AI organizes the assessment; the qualified ophthalmic surgeon makes the clinical decision and performs surgery.
CER-AI is a clinical decision support platform for preoperative corneal ectasia risk screening and refractive surgery evaluation. It analyzes uploaded Pentacam images to support ophthalmologists assessing candidates for LASIK, PRK, and SMILE. AI assists image reading; separate rule-based pathways organize the risk assessment for surgeon review.
Refractive surgery screening for LASIK and PRK
CER-AI supports preoperative refractive surgery screening before laser vision correction. Its LASIK screening software and PRK screening software organize Pentacam findings, independent ectasia-risk pathways and procedure-specific corneal tissue-safety checks for surgeon review.
The full product name is Corneal Ectasia Risk Assessment Intelligence. This is the canonical CER-AI product page. CER-AI presents imaging measurements, independent risk pathways, tissue-safety checks and an explained assessment report in one workflow without mathematically combining the pathway results.
Who may be unsuitable for laser eye surgery, and when is it deferred?
Potentially unsuitable: Keratoconus or corneal ectasia, corneal anatomy that cannot support a safe tissue plan, advanced or uncontrolled eye disease, and uncontrolled systemic disease affecting healing may preclude standard laser vision correction.
Usually deferred: Age under 18, an unstable prescription, pregnancy or breastfeeding, active eye infection or inflammation, and significant untreated dry eye or eyelid disease. Treat the condition or establish stable measurements before reassessment. Review medications affecting healing; patients should not stop prescribed medication themselves.
Procedure-specific decision: Being unsuitable for LASIK does not automatically establish suitability for PRK or transepithelial PRK. Thin corneas alone do not exclude every procedure; review topography, tomography and remaining tissue together. Controlled diabetes or autoimmune disease requires individualized review of the disease, ocular findings and device instructions.
CER-AI supports review of corneal findings and tissue planning. This summary is not individual surgical clearance; the ophthalmic surgeon makes the final decision.
Sources (accessed October 4, 2026): FDA — LASIK suitability; ESCRS refractive surgery recommendations (page marked draft/concept version); Systematic review of PRK in thin corneas.
How is the safety of laser eye surgery assessed?
Suitability for laser vision correction is assessed through a comprehensive eye examination, prescription stability, corneal topography and tomography, corneal thickness and the tissue expected to remain after the planned procedure. No single test or normal thickness measurement establishes safety by itself, and screening cannot guarantee zero risk.
- Examination and history: Review age, refractive changes, dry eye and the ocular surface, other eye disease, previous surgery, medications and general health. Assess pupils and expectations for night vision.
- Corneal screening: Review corneal shape, anterior and posterior surfaces and thickness distribution for findings suspicious for subclinical keratoconus or ectasia. Repeat questionable or inconsistent measurements when needed.
- Procedure-specific tissue planning: Separately review the intended correction, optical zone, tissue removal and remaining corneal tissue for LASIK or PRK. Suitability for one procedure does not automatically establish suitability for another.
- Surgeon decision: The ophthalmic surgeon weighs the findings and risks to decide whether to proceed, consider another approach or defer treatment.
How does CER-AI support this assessment?
CER-AI assists with reading Pentacam reports using artificial intelligence. The surgeon checks measurements against their sources; ERSS, Final BAD-D, NICE and PS3 remain independently interpretable, with tissue-safety calculations reviewed separately. The software organizes the assessment and its reasoning. It does not replace examination, authorize surgery autonomously or guarantee freedom from complications.
Medical sources: FDA — LASIK suitability and LASIK risks. These general sources do not establish validation of CER-AI as a complete product.
Clinical problem addressed
Postoperative corneal ectasia is a major safety concern in corneal refractive surgery. Preoperative screening therefore examines multiple domains rather than relying on a single measurement. These domains can include anterior corneal topography, corneal tomography, pachymetry, refractive magnitude, age, residual stromal bed and other procedure-specific factors.
Corneal ectasia screening before refractive surgery
For a refractive surgeon, a corneal ectasia risk assessment is not simply a search for an abnormal topography label. It asks whether the complete preoperative evidence supports proceeding with LASIK or PRK, changing the proposed procedure, obtaining better-quality or longitudinal data, or deferring treatment.
CER-AI is designed for this physician workflow. It organizes preoperative ectasia screening across corneal topography and tomography, pachymetry, refractive and age-related factors, independent ERSS, BAD-D, NICE and PS3 pathways, and procedure-specific tissue safety. Pentacam ectasia screening is therefore one evidence source within the assessment—not a replacement for clinical examination or surgeon judgment.
Post-LASIK ectasia risk assessment and keratoconus screening review both depend on the quality and interpretation of preoperative evidence. CER-AI helps the surgeon examine susceptibility before surgery; it does not diagnose keratoconus or predict an individual patient's postoperative outcome.
Clinicians evaluating LASIK ectasia risk can review the corneal ectasia screening guide, examine worked synthetic cases, and trace the underlying claims through the clinical evidence map and medical reference registry.
What should surgeons check when evaluating software for ectasia assessment?
Check whether the software shows its measurement sources, keeps risk pathways interpretable, identifies missing or conflicting values, separates tissue safety from ectasia susceptibility, and explains its validation limits. These are features to review alongside clinical evidence and the surgeon's own examination.
AI-assisted corneal topography and tomography evaluation
Artificial intelligence helps read measurements from uploaded Pentacam reports for surgeon review. These source measurements feed separate, transparent clinical assessment rules.
Preoperative screening for post-LASIK ectasia risk
This workflow reviews susceptibility before LASIK or PRK. It is not a postoperative screening service for previously operated corneas.
AI-assisted keratoconus screening review
Corneal imaging findings and independent risk pathways support the surgeon’s assessment of keratoconus susceptibility; the software does not make an autonomous diagnosis.
How does CER-AI use artificial intelligence?
AI assists with reading information from supplied Pentacam images. Extracted measurements can be incorrect, incomplete or conflicting; source review and correction remain essential parts of professional use.
Clinical risk classification and tissue-safety calculations are handled separately by the canonical rule-based assessment engine. AI-assisted image reading is not a claim that CER-AI is an externally validated autonomous diagnostic or ectasia-prediction model.
Final BAD-D is read from the Pentacam display. CER-AI does not acquire the corneal scan, replace the Pentacam device or reconstruct its proprietary indices.
Risk pathways represented in CER-AI
Randleman / ERSS
The Randleman Ectasia Risk Score System is represented as an independent clinical risk pathway using its defined component structure and anterior-topography evidence.
Final BAD-D
Pentacam Belin/Ambrosio Final BAD-D is treated as an independent tomographic signal rather than being mathematically blended into ERSS.
NICE
The NICE pathway is evaluated separately using the required corneal tomography inputs and an auditable component assessment.
PS3
PS3 adds another independently visible risk pathway with procedure-aware interpretation of selected corneal, refractive and inter-eye findings.
From Pentacam images to an assessment report
The workflow starts with the required examination images and clinical inputs. Measurements are linked to defined source fields; missing or conflicting decision-critical data are identified for completion or confirmation. ERSS, Final BAD-D, CER-AI-adapted NICE and PS3 are then presented as independent pathways alongside separate procedure-safety checks.
The report documents the assessment, reasons, warnings and applicable planning information. It supports the surgeon's review rather than declaring that surgery is risk-free. PDF and Word reporting use the already-computed canonical report payload; the public website does not calculate a separate assessment.
Tissue-safety assessment remains separate
A reassuring ectasia-risk pathway does not automatically establish procedural safety. CER-AI separately evaluates treatment-related tissue constraints, including pachymetry, anticipated ablation, residual stromal bed or residual stromal tissue, planned refractive correction and postoperative keratometric safety.
Why the pathways remain independent
Independent presentation makes disagreement between risk systems visible. It also allows the clinician to identify which observation or missing input is responsible for a caution or stop decision instead of receiving only a single opaque composite score.
Frequently asked questions about CER-AI
Is CER-AI a single corneal ectasia score?
No. CER-AI keeps ERSS, BAD-D, NICE and PS3 independently visible and separately interpretable. Tissue and procedure-safety calculations are also presented separately rather than being hidden inside one proprietary score.
Which Pentacam images does a CER-AI assessment require?
The current bilateral workflow requires five Pentacam sources: 4 Maps Refractive for OD and OS, Belin/Ambrósio BAD Display for OD and OS, and one Show 2 Exams Topometric comparison. A treatment card is optional; when it is absent or unreadable, the surgeon supplies the required manifest and intended refraction.
Who is CER-AI designed for?
CER-AI is intended for qualified ophthalmologists and refractive surgeons performing structured preoperative screening. It is not a patient self-assessment tool.
How does CER-AI handle missing or unreadable information?
Decision-critical values remain linked to defined source fields. When a required value cannot be obtained reliably, the workflow identifies the missing field for surgeon completion instead of silently inventing a value.
Does CER-AI decide whether surgery should be performed?
No. CER-AI organizes evidence, applies predefined assessment and safety rules, and documents the reasoning. The final clinical and surgical decision remains the surgeon's responsibility.
Has the complete CER-AI software been externally validated?
The public evidence pages identify literature supporting individual clinical concepts and risk pathways. Those publications do not constitute external validation of CER-AI as a complete software product. CER-AI does not claim validated diagnostic sensitivity, specificity or superiority unless supporting CER-AI-specific evidence is explicitly published.
AI-assisted software for subclinical keratoconus assessment
CER-AI helps ophthalmologists review findings that may raise suspicion of subclinical keratoconus before LASIK or PRK. It supports the clinician’s diagnostic assessment by organizing Pentacam topography and tomography findings, including corneal asymmetry, thickness distribution and the device-reported Final BAD-D.
Artificial intelligence assists with reading uploaded Pentacam reports; separate, transparent rule-based algorithms organize the clinical risk assessment. Subclinical keratoconus screening is not a confirmed diagnosis. The ophthalmologist interprets the imaging together with the examination and, when needed, repeat or longitudinal measurements. CER-AI does not independently diagnose or exclude keratoconus, and validated CER-AI-specific diagnostic sensitivity or specificity is not claimed.
Research on Pentacam topographic and tomographic indices in subclinical and clinical keratoconus
Corneal ectasia diagnosis and the role of CER-AI
Corneal ectasia diagnosis is a clinical determination made by an ophthalmologist. CER-AI supports review of Pentacam topography and tomography reports and organizes ectasia risk findings for the surgeon. Preoperative risk screening is not the same as diagnosing established disease. CER-AI does not provide an autonomous diagnosis or replace clinical examination and assessment of progression.
Evidence-based answers for refractive surgeons
Read what is recommended for corneal ectasia screening before refractive surgery and review the neutral comparison of ectasia screening systems and their roles.
How a CER-AI assessment works
- Upload the OD and OS 4 Maps Refractive and BAD Display images, plus one Show 2 Exams Topometric comparison.
- Review the source measurements; the surgeon completes required missing or unreadable fields.
- Inspect ERSS, BAD-D, NICE and PS3 independently alongside the tissue-safety calculations.
- Review the explanation and report. The final clinical and surgical decision remains with the surgeon.
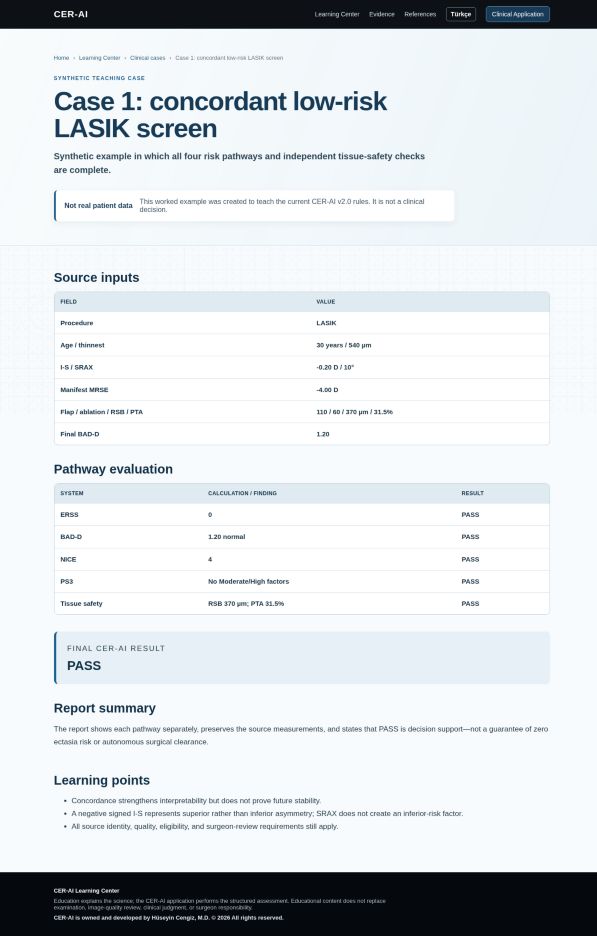
Synthetic teaching example
Not real patient data or a generated clinical report. PASS does not mean zero risk or surgical clearance.
Case 1: concordant low-risk LASIK screen
| Procedure | LASIK |
|---|---|
| Age / thinnest | 30 years / 540 µm |
| I-S / SRAX | -0.20 D / 10° |
| Manifest MRSE | -4.00 D |
| Flap / ablation / RSB / PTA | 110 / 60 / 370 µm / 31.5% |
| Final BAD-D | 1.20 |
| ERSS | 0 | PASS |
|---|---|---|
| BAD-D | 1.20 normal | PASS |
| NICE | 4 | PASS |
| PS3 | No Moderate/High factors | PASS |
| Tissue safety | RSB 370 µm; PTA 31.5% | PASS |
The report shows each pathway separately, preserves the source measurements, and states that PASS is decision support—not a guarantee of zero ectasia risk or autonomous surgical clearance.
View the teaching-example screenshot
Can I examine an example before using the application?
Explore the public worked examples to see how inputs, independent pathway results and explanations fit together. These are synthetic educational cases, not live analyses or actual patient reports. No patient upload is needed to read them.
Explore worked examples · Read the methodology and evidence boundaries · Review the required Pentacam sources
Continue with the CER-AI Learning Center, review the clinical evidence mapped to CER-AI, or search the complete medical reference registry.